

Abstract
Periodontitis is a chronic inflammatory disease of the tooth-supporting tissues whose principal microbial driver, Porphyromonas gingivalis, has been detected repeatedly in the brains of people with Alzheimer's disease. This narrative review synthesizes the evidence linking periodontitis to Alzheimer's disease through P. gingivalis, its gingipain proteases and neuroinflammation, drawing on epidemiological cohorts and meta-analyses, postmortem human studies and experimental models published between 2018 and 2025. Umbrella and conventional meta-analyses estimate that periodontitis and tooth loss raise the risk of cognitive disorders by 51% to 65%, although residual confounding limits causal inference. Postmortem studies localize gingipains to neurons and to tau and ubiquitin pathology, and experimental oral infection of wild-type mice and rats reproduces amyloid-beta and tau lesions that depend on gingipain activity. Mechanistically, the bacterium reaches the central nervous system through bacteremia, the trigeminal nerve and outer membrane vesicles, and gingipains open the blood-brain barrier and activate microglia through protease-activated receptor 2, sustaining neuroinflammation. Gingipain inhibitors reduce pathology in animal models and have reached clinical trials, although the phase 2/3 GAIN trial missed its primary endpoint in the overall population. Periodontal treatment is biologically plausible but remains unproven for cognitive protection. Neuroinflammation is supported as a mechanistic bridge, while causation in humans remains to be demonstrated.
Keywords
Alzheimer disease, periodontitis, Porphyromonas gingivalis, gingipains, neuroinflammation
INTRODUCTION
Alzheimer's disease is the most common cause of dementia and a leading cause of disability and death in older adults, with total healthcare costs estimated at $305 billion in the United States in 2020 and projected to rise beyond one trillion dollars as the population ages.(1,2) Periodontitis, a chronic inflammatory disease of the tooth-supporting tissues driven by a dysbiotic subgingival biofilm, affects approximately 19% of the global adult population and is among the most prevalent chronic infections worldwide, and periodontal problems reach more than 70% of adults aged 65 years or older.(3,4) The two conditions share advanced age as a risk factor and a common substrate of low-grade, persistent inflammation, which has motivated the hypothesis that oral infection contributes to neurodegeneration.(5) Because periodontitis is detectable, treatable and modifiable, any causal connection between the two conditions carries immediate implications for dental practice and for the prevention of cognitive decline in aging populations.
Evidence accumulated over the past decade has moved this hypothesis from speculation toward a testable biological model. Postmortem studies detected DNA and proteases of Porphyromonas gingivalis, the keystone pathogen of periodontitis, in the brains of people with Alzheimer's disease, and experimental oral infection of wild-type mice reproduced amyloid-beta deposits, tau pathology and cognitive deficits.(6,7) Several meta-analyses of observational cohorts have quantified the epidemiological association between periodontitis, tooth loss and cognitive decline, and long-standing periodontitis of ten or more years has been reported to double the risk of the sporadic form of the disease.(8,9) These convergent signals have made the oral cavity a focus of the broader effort to identify modifiable risk factors for dementia. Despite this progress, the causal pathway remains unsettled: some cohort analyses report weak or null associations once confounders are accounted for, and the field continues to debate whether periodontal bacteria initiate, accelerate or merely accompany neurodegeneration.( 10,11)
What has been synthesized less consistently is the specific mechanistic role of the gingipains, a family of cysteine proteases that concentrate the neuropathogenic potential of P. gingivalis, and the position of neuroinflammation as the bridge between gingipain activity and neuronal damage. Gingipains cleave host proteins, degrade tight junction components of the blood-brain barrier, activate microglial receptors and localize to neurons and to tau pathology in postmortem brains.(12-14) A therapeutic proof of concept has also begun to emerge from gingipain inhibitors, although the clinical results have been mixed.(15,16) This gap matters because the gingipains are both candidate markers of oral-systemic transmission and tractable drug targets, and because a mechanistic account of the axis would clarify which patients should be monitored and which interventions deserve priority.
The objective of this review is to synthesize the current evidence on the association between periodontitis and Alzheimer's disease, with emphasis on the role of P. gingivalis and its gingipain proteases in neuroinflammation. Four questions guide the synthesis: how strong is the epidemiological evidence; through which routes do the bacterium and its products reach the brain; how do gingipains drive neuroinflammation and neurodegeneration; and what do gingipain inhibition and periodontal treatment offer for prevention and therapy.
METHODS
This narrative review was prepared according to the Scale for the Assessment of Narrative Review Articles, with a documented but non-exhaustive search strategy and an explicit scheme for organizing the synthesis.
The review is organized into five thematic axes that follow the biological sequence from oral infection to neurodegeneration. It does not claim systematic exhaustiveness and does not report screening counts or a PRISMA flow. The synthesis is qualitative, given the heterogeneity of the study designs involved, and it deliberately separates epidemiological, postmortem, experimental and clinical evidence so that the strength of each strand can be assessed independently.
Literature was identified in OpenAlex and PubMed using combinations of the terms "Porphyromonas gingivalis", "gingipain", "periodontitis", "Alzheimer disease", "neuroinflammation", "cognitive decline", "blood-brain barrier" and "gingipain inhibitor". The core search covered publications from 2018 to 2025, the window established for this review. Supporting literature without a lower date limit was used to contextualize classical mechanisms and methodological concepts, and reference lists of the retrieved reviews were inspected for additional sources. Duplicate records across the two databases were merged before screening, and retrieval was not restricted by language at the search stage. Searches that returned no usable records were rerun with alternative terms rather than interpreted as absence of literature.
Studies were retained when they reported primary data or meta-analytic estimates on the epidemiological association between periodontitis or tooth loss and cognitive outcomes, on the detection of P. gingivalis or gingipains in human brain tissue, on experimental infection of animal or cell models with P. gingivalis, or on gingipain inhibition. Narrative and systematic reviews were used principally to compare interpretations in the Discussion. Records whose abstracts were not available in English or Spanish were not synthesized in detail, which may restrict the geographic coverage of the synthesis.
Findings were organized into five axes: the epidemiological association; translocation and brain colonization; gingipains as virulence factors and their neuronal targets; neuroinflammation as the mechanistic bridge; and therapeutic implications. For each axis, the main claims and the studies that support or contradict them were recorded in an argument matrix, and the type and level of evidence were appraised. Table 1 summarizes this synthesis.
The level and type of evidence supporting each claim were appraised qualitatively, distinguishing meta-analytic estimates from single cohorts, human postmortem observations from animal experiments, and phase 1 from phase 2/3 trial data. Because this is a narrative review, no formal risk-of-bias tool was applied; instead, the direction and magnitude of each finding were weighed against the studies that oppose it, as recorded in the argument matrix. This appraisal is reflected in the wording of the Development section and in the synthesis table. No ethical approval was required, because the review used only published literature.
DEVELOPMENT
The five axes are synthesized in Table 1 and integrated in the conceptual model of Figure 1, which positions the gingipains as the molecular link between oral infection and neuroinflammation. (Table 1)
Axis | Key findings | Representative studies | Type of evidence |
|---|---|---|---|
Epidemiological association | Periodontitis and tooth loss associate with cognitive decline and dementia (OR 1.65 and 1.51 in an umbrella meta-analysis); associations weaken after confounder adjustment | Qadir et al. 2025; Guo et al. 2021; Nilsson et al. 2018; Asher et al. 2025 | Meta-analyses and prospective cohorts |
Translocation and brain colonization | Pg DNA and gingipains found in postmortem brains; BBB opened through Mfsd2a/Caveolin-1 transcytosis and tight junction degradation | Dominy et al. 2019; Lei et al. 2023; Nonaka et al. 2022 | Human postmortem, animal and in vitro BBB models |
Gingipains and neuronal targets | Gingipains cleave host substrates, localize to neurons and tau pathology, and their activity is required for neuropathology | Dominy et al. 2019; Haditsch et al. 2020; Mieszkowska et al. 2025 | Enzymatic assays, iPSC neurons, zebrafish |
Neuroinflammation | Pg and gingipains activate microglia through PAR2 and induce oxidative and mitochondrial injury with age-dependent cognitive impairment | Ding et al. 2018; Nonaka et al. 2020; Verma et al. 2023 | Mouse and cell models |
Therapeutic implications | Gingipain inhibitors reduce pathology in models; the GAIN phase 2/3 trial missed its primary endpoint; periodontal treatment is plausible but unproven | Sabbagh et al. 2022; Detke et al. 2021; Yavuz et al. 2025 | Clinical trial reports and animal interventions |
Note: AD = Alzheimer's disease; BBB = blood-brain barrier; Pg = Porphyromonas gingivalis; OR = odds ratio; PAR2 = protease-activated receptor 2. Source: Elaborated by the authors from the reviewed studies.
Figure 1 depicts the proposed sequence from chronic periodontitis to neurodegeneration, in which translocation, gingipain activity and neuroinflammation precede and sustain the amyloid and tau lesions that define the clinical syndrome. (Figure 1)
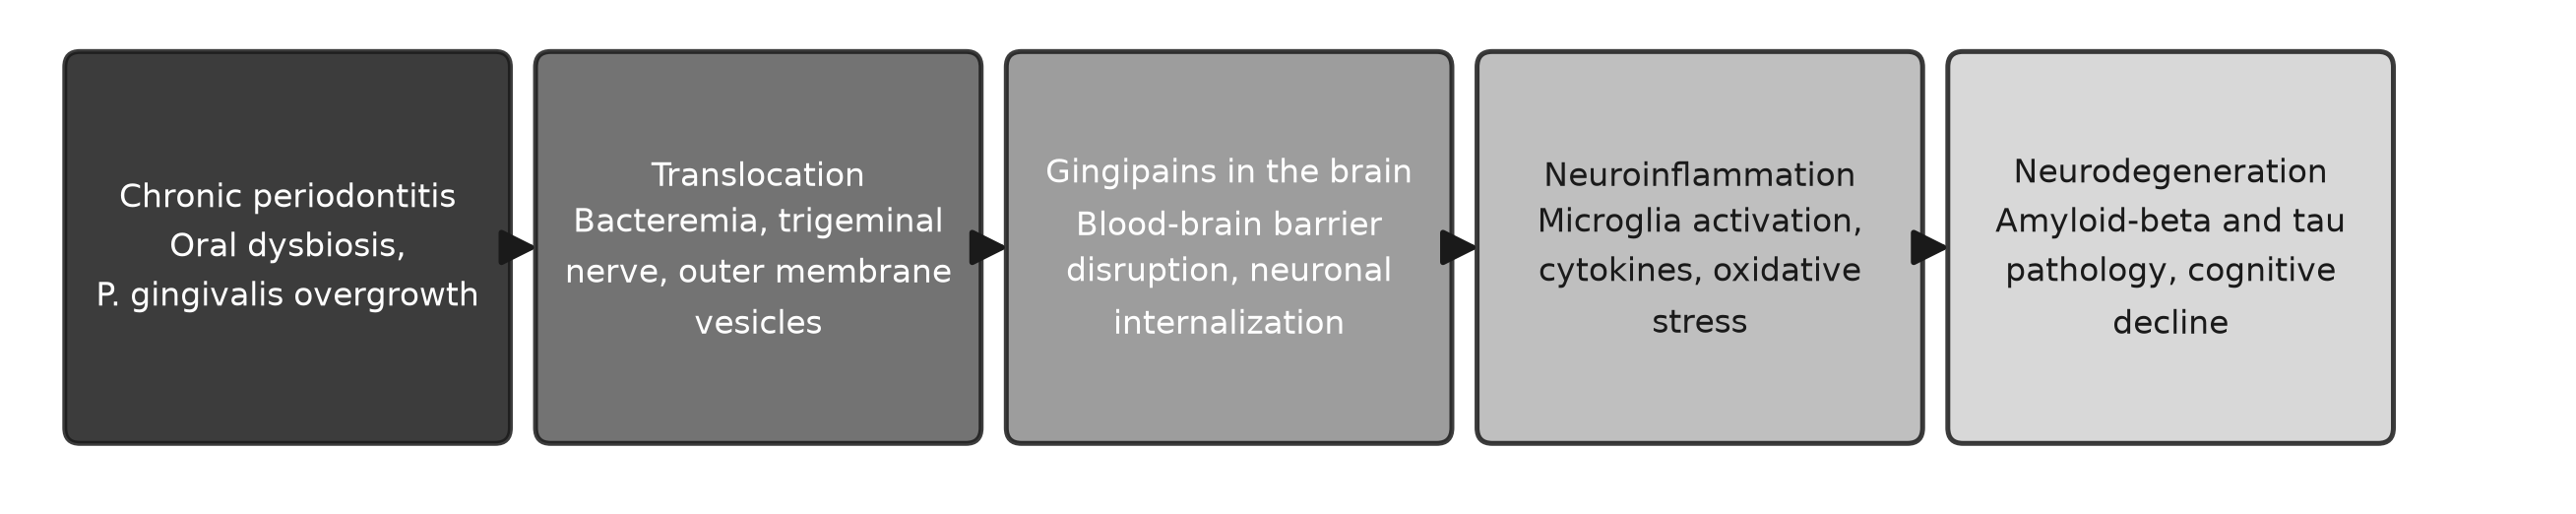
Figure 1. Conceptual model of the periodontitis-Alzheimer's disease axis.
Note: The model represents the proposed sequence from chronic periodontitis to neurodegeneration, with gingipains as the link between oral infection and neuroinflammation. Source: Elaborated by the authors.Epidemiological association between periodontitis, tooth loss and cognitive decline
The most recent synthesis, an umbrella meta-analysis of 20 meta-analyses, estimated that periodontitis and tooth loss increase the odds of cognitive disorders by 65% (OR 1.65, 95% CI 1.37-1.97) and 51% (OR 1.51, 95% CI 1.32-1.71), respectively, and that severe periodontitis carries an odds ratio of 2.69 (95% CI 2.26-3.20); pooled cohort analyses yielded a relative risk of 1.26 (95% CI 1.20-1.32), with low to moderate certainty of evidence graded by GRADE.(8) Earlier meta-analyses reached similar conclusions: periodontitis was associated with cognitive impairment with an OR of 1.77 (95% CI 1.31-2.38), although the association with dementia did not reach statistical significance in one pooled estimate (OR 1.59, 95% CI 0.92-2.76), and moderate or severe periodontitis was the category most clearly associated with dementia.(17) A meta-analysis of 18 cohorts with 356,297 participants found that tooth loss increased the risk of dementia by 15% (RR 1.15, 95% CI 1.10-1.20) and of cognitive decline by 20% (RR 1.20, 95% CI 1.14-1.26), with subgroup estimates of 12% for Alzheimer's disease and 25% for vascular dementia and substantial heterogeneity across cohorts.(18)
Prospective cohorts support a longitudinal association. In the Swedish National Study on Ageing and Care, periodontitis defined as 4 mm or more of bone loss at at least 30% of tooth sites was associated with a decline of three or more points on the Mini-Mental State Examination over six years after confounder adjustment.(19) In the Colombian PerioMind cohort, participants with mild cognitive impairment showed higher gingival erythema and pocket depth scores, and a predictive model identified gingival erythema, the presence of periodontitis and pocket depth as the metrics most strongly associated with impairment.(20) In the Health 2000 and 2011 surveys, moderate periodontitis was cross-sectionally associated with lower overall cognition (OR 1.19, 95% CI 1.02-1.40), and posterior tooth loss and loss of posterior occlusal support were associated with 15-year incident dementia with hazard ratios between 1.99 and 2.89.(10,21)
Neuroimaging and mediation analyses extend the association beyond cognitive scales. In the Washington Heights-Inwood Columbia Aging Project, greater periodontitis extent was associated with lower entorhinal cortex volume and lower cortical thickness on brain magnetic resonance imaging, and a higher number of retained teeth with higher entorhinal volume and cortical thickness.(22) In the National Health and Nutrition Examination Survey, a pro-inflammatory diet was estimated to mediate between 9.2% and 36.4% of the association between periodontitis and cognitive dysfunction, and serum vitamin D between 8.1% and 73.2%, which indicates that systemic inflammation and nutrition account for part, but not all, of the association.(23) Systematic reviews that focused on confounders reached the same conclusion: the association is consistent, but its magnitude shrinks when education, comorbidity and socioeconomic position are modeled.(24,25)
The main divergence concerns strength and causality. The aims of the Health 2000 analyses note explicitly that findings for periodontitis remain inconclusive when tooth loss is separated, and residual confounding by diet, diabetes and education cannot be excluded in any observational design.(10) The certainty of the evidence was rated low to moderate in the umbrella review.(8) The epidemiological data are therefore best read as establishing a plausible, dose-responsive association, in which severe and long-standing disease carries the highest risk, rather than a demonstrated causal effect.
Taken together, these data support a dose-response pattern in which the severity and duration of periodontal exposure matter more than its mere presence. Severe periodontitis carried an odds ratio of 2.69 in the umbrella review, and posterior tooth loss, a marker of advanced disease, showed the largest hazard ratios in the Finnish cohorts, while earlier and milder disease produced smaller or null estimates.(8,21) This pattern is consistent with a cumulative exposure model, in which the repeated entry of bacterial products into the circulation over years, rather than a single episode, drives the cerebral consequences. It also aligns with the observation that the association is strongest in older adults, in whom both periodontal destruction and preclinical neurodegeneration have had time to accumulate.( 19)
Beyond the pooled estimates, the exposure itself is measured inconsistently. Studies define periodontitis by pocket depth, clinical attachment loss, radiographic bone loss or self-report, and these definitions do not capture the same disease severity.(24) Tooth loss, the outcome used by several cohorts, is a composite that conflates periodontitis, caries and traumatic extraction, which may partly explain the heterogeneity observed in the meta-analyses.(18) Standardizing periodontal case definitions, and reporting disease duration, would make future epidemiological work more comparable and would sharpen the dose-response estimates that currently depend on severity gradients.
Translocation and brain colonization of Porphyromonas gingivalis
The most direct evidence comes from postmortem human tissue. Dominy and colleagues detected P. gingivalis DNA and gingipain proteases in the brains of people with Alzheimer's disease, where gingipain load correlated with tau and ubiquitin pathology, and a related series identified the same proteases in more than 90% of Alzheimer's disease brains.(6,14) Ultrastructural studies extended this localization to dopaminergic neurons of the substantia nigra, where gingipains associated with the periphery of alpha-synuclein aggregates and cleaved recombinant alpha-synuclein in vitro, showing that the proteases are not restricted to the neocortex.(26) These observations establish presence, not timing: they cannot distinguish a causal agent from a commensal that colonizes tissue already damaged by disease.
The bacterium can reach the central nervous system by several routes. Repeated tail-vein injection of P. gingivalis in rats increased brain extravasation of Evans blue and albumin and opened the blood-brain barrier through a transcytosis pathway involving Mfsd2a and Caveolin-1.(27) Outer membrane vesicles, which package gingipains and lipopolysaccharide, are proposed as vehicles that carry virulence factors across endothelial barriers, and they have been linked to the systemic spread of the bacterium beyond the oral cavity.(3,28) In mice, gingival exposure to P. gingivalis or its extracellular vesicles, but not gavage, produced memory impairment and increased hippocampal markers of microglial activation, implicating the trigeminal route and the periodontal pocket as the relevant portal of entry.(29) Outer membrane vesicles have been described as the most plausible transport mechanism for bacterial material into the brain in this context.(9)
Gingipains directly compromise the barrier. Secreted gingipains increased the permeability of human cerebral microvascular endothelial monolayers by degrading the tight junction proteins zonula occludens-1 and occludin, and a gingipain-deficient strain caused a significantly smaller reduction of both proteins.(12) In zebrafish larvae, systemic infection with wild-type P. gingivalis increased barrier permeability and reduced claudin-5 and zonula occludens-1 on cerebral vessels, an effect absent in larvae infected with a gingipain-deficient mutant; tight junction gene expression did not change, which indicates post-translational degradation of the proteins.(30) These convergent findings from three model systems identify gingipain activity, rather than the whole bacterium alone, as the principal determinant of barrier damage.
Once translocated, the bacterium reproduces features of Alzheimer neuropathology in animals. Chronic oral application of P. gingivalis for 22 weeks in wild-type mice induced neuroinflammation, microgliosis, astrogliosis, and intra- and extracellular amyloid plaques and neurofibrillary tangles.(7) The effect is strain-dependent: encapsulated, more virulent serotypes triggered Alzheimer-like pathology in wild-type rats,(31) and co-infection with Treponema denticola increased all seven brain pathologies examined in chronically inoculated mice, which points to synergistic virulence between periodontal pathobionts.(32) In obese diabetic mice, oral P. gingivalis infection produced reactive microglia and astrocytes and tau immunopositivity, although silver-stained plaques and tangles were not detected, suggesting that metabolic comorbidity modulates the neuropathological response.(33)
Transient bacteremia is the event that connects the periodontal pocket to distant organs. Daily activities such as chewing and tooth brushing release oral bacteria into the bloodstream, and P. gingivalis is adapted to survive this journey by invading and persisting within host cells and by modulating the immune response to avoid clearance.(28) This intracellular lifestyle helps explain why the organism and its products appear in tissues far from the oral cavity, including the brain of people with Alzheimer's disease.(27) The periodontal pocket therefore functions as a reservoir from which small, repeated inocula enter the circulation throughout adult life, a model that fits the dose-response pattern observed in the epidemiological data.
The bacterium also contributes to systemic inflammation that may act on the brain independently of direct colonization. Periodontitis sustains a low-grade inflammatory state that is itself a recognized correlate of cognitive decline, and its pathogens release cytokines that reach the central nervous system through the circulation.(34) Lipopolysaccharide and other surface virulence factors of P. gingivalis stimulate Toll-like receptors on immune and endothelial cells, linking the periodontal infection to the vascular and immune changes that precede cerebral involvement.(35) Direct invasion and systemic inflammation are therefore best regarded as complementary, not competing, explanations of how the oral pathogen reaches and injures the brain.
Gingipains: virulence factors with neuronal targets
Gingipains are a family of secreted and membrane-bound cysteine proteases, comprising the arginine-specific gingipains RgpA and RgpB and the lysine-specific gingipain Kgp, that account for much of the proteolytic activity of P. gingivalis.(36) They degrade extracellular matrix proteins, complement components and cytokines, and they cooperate with bacterial peptidyl arginine deiminase to citrullinate host proteins, a mechanism linked to rheumatoid arthritis and relevant to immune evasion.(36) Their interactions with host cells are partly transduced through Toll-like receptors, which explains the pro-inflammatory response they elicit in periodontal and systemic tissues.(35)
In neurons, gingipains have direct intracellular targets. Infection of human induced pluripotent stem cell-derived neurons with P. gingivalis produced intracellular bacteria and persistent gingipain expression, with time-dependent neuronal death.(14) The observation that gingipains localize to the neuronal cytoplasm in postmortem brains, where their load parallels tau and ubiquitin pathology, places the proteases within the same compartment as the misfolded proteins that define the disease.(6) In the substantia nigra, lysine-gingipain cleaved alpha-synuclein, and this finding indicates that gingipain substrates include proteins that aggregate in neurodegeneration.(26)
An additional layer concerns amyloid-beta itself. Amyloid-beta oligomers have broad antimicrobial activity, and P. gingivalis is opsonized by amyloid-beta 42, which supports the hypothesis that amyloid deposition represents, at least in part, a host antimicrobial response that becomes pathogenic when the inflammatory response escapes control.(15,37) Under this view, gingipains are not bystanders but agents that both damage neurons and provoke the protein aggregation that defines Alzheimer's disease.
The two enzymatic specificities are complementary. The arginine-specific gingipains and the lysine-specific gingipain cleave distinct host substrates and act synergistically, which is why dual inhibitors that block both activities perform better than single-target compounds in preclinical models.(36,38) By generating fragments from matrix, complement and cytokine proteins, the enzymes remodel the host environment and modulate immunity.(36) The demonstration that gingipains localize to neurons, and that their inhibition prevents pathology in animal models, converts these enzymatic properties into a coherent account of how a periodontal pathogen could influence the brain.(6,14)
Tau provides the clearest link between gingipain load and the neuropathology used to stage Alzheimer's disease. Gingipain load correlates with tau and ubiquitin pathology in postmortem brains, and experimental infection increases phosphorylated tau in animal models, which suggests that the proteases engage the tau pathway rather than only the amyloid pathway.(6,39) Because tau spread tracks clinical progression more closely than amyloid burden, this connection is mechanistically significant: it implies that gingipain activity, if it operates early, could influence the lesions that best predict cognitive decline.(40)
Neuroinflammation as the mechanistic bridge
Neuroinflammation is the most consistently reproduced intermediate between gingipain activity and neuronal loss. Oral infection with P. gingivalis impaired learning and memory and raised brain levels of tumor necrosis factor-alpha, interleukin-6 and interleukin-1 beta in middle-aged mice, whereas young mice were spared, which indicates that the response is age-dependent.(41) This pattern matches the epidemiological observation that the risk of dementia rises with the duration of periodontal exposure and with age.
At the cellular level, gingipains activate microglia through protease-activated receptor 2. Secreted gingipains induced migration and membrane ruffling of the human microglial cell line HMC3 through this receptor, an effect abolished by gingipain inhibitors and dependent on Src kinase and beta-arrestin.( 13) Activated microglia are the main source of the pro-inflammatory cytokines that accompany amyloid and tau lesions, and their sustained activation is recognized as a driver and not only a downstream consequence of neurodegeneration.( 40)
Lipopolysaccharide from P. gingivalis contributes an oxidative component. Treatment of neural cells with the endotoxin activated Toll-like receptor 4, increased reactive oxygen species, reduced mitochondrial membrane potential and repressed genes involved in mitochondrial biogenesis, linking the bacterium to mitochondrial dysfunction.(4) Mitochondrial failure is a plausible mechanism by which chronic inflammation translates into synaptic and neuronal loss, and it connects the oral pathogen to the metabolic alterations repeatedly documented in Alzheimer's disease.(40)
Peripheral and brain-wide effects converge on this axis. Oral administration of P. gingivalis altered the gut microbiota and impaired glymphatic clearance while producing cognitive deficits, suggesting that the oral pathogen acts on the brain both directly and through the gut-brain axis.(42) Consistent with a causal role of dysbiosis, the lantibiotic nisin reduced periodontal pathogen DNA, pro-inflammatory cytokines and amyloid-beta 42 and tau in the brain of a polymicrobial mouse model of periodontitis.(43) Reviews that integrate these pathways conclude that neuroinflammation is the common effector through which periodontal pathogens, and P. gingivalis in particular, influence neurodegeneration.(34,44)
The relationship between inflammation and protein pathology is bidirectional. Aggregated amyloid-beta and hyperphosphorylated tau themselves activate microglia and sustain the inflammatory response, so an initial infectious or inflammatory insult can set in motion a cycle that continues after the inciting stimulus has been removed.(40) This self-amplifying loop is compatible with the observation that gingipain load correlates with tau and ubiquitin pathology in postmortem brains without proving that the proteases caused the lesions.(6) It also implies that interrupting neuroinflammation, rather than eliminating the bacterium alone, may be necessary to halt progression once the cycle is established.
Systemic markers corroborate the neuroinflammatory account. Periodontal pathogens raise circulating pro-inflammatory cytokines, and the resulting systemic state is considered one route by which oral dysbiosis influences the brain in the absence of direct invasion.(34) The distinction between direct and systemic routes is clinically relevant, because it predicts different responses to treatment: eliminating the pathogen should reduce both, whereas measures that only dampen systemic inflammation would leave the microbial reservoir intact.(44) Both routes, however, converge on the same microglial and mitochondrial endpoints described above.
Therapeutic implications of gingipain inhibition and periodontal treatment
Gingipain inhibition provides the most direct test of the hypothesis. Small-molecule inhibitors that target the active sites of Rgp and Kgp reduced P. gingivalis brain load and amyloid-beta pathology in wild-type mice.( 6) A systematic review identified seven preclinical studies, all with favorable outcomes on inflammation, bacterial load and tissue destruction, and no clinical studies completed; dual inhibitors of Rgp and Kgp were more effective than single-target compounds.( 38)
The clinical translation has been more difficult. Atuzaginstat (COR388), an irreversible lysine-gingipain inhibitor, was well tolerated in phase 1 and advanced to the phase 2/3 GAIN trial, which randomized 642 participants with mild to moderate Alzheimer's disease to 40 or 80 mg twice daily or placebo for 48 weeks, with co-primary endpoints of cognitive and functional decline.(15,16) The trial did not meet its primary endpoints in the overall intent-to-treat population; prespecified subgroups defined by P. gingivalis-positive saliva showed evidence of slowed cognitive decline, but the program was discontinued after a hepatic safety signal.(45) A second-generation, brain-penetrant lysine-gingipain inhibitor, LHP588, has completed single and multiple ascending dose studies in healthy volunteers, and a phase 2b study was planned.(45)
The results of the GAIN program carry a methodological lesson for future trials. Because efficacy was suggested only in prespecified subgroups with detectable oral P. gingivalis, patient selection based on pathogen load, rather than on clinical stage alone, is likely to be decisive for gingipain-targeted therapy.(45) Biomarkers that quantify gingipain activity in saliva, serum or cerebrospinal fluid would allow enrichment and provide pharmacodynamic evidence of target engagement, which the first-generation program lacked.(15,38) Until such biomarkers are validated, the interpretation of negative trials remains ambiguous: they may reflect an inactive target, an unselected population or insufficient exposure.
The gingipain programs sit within a broader effort to treat Alzheimer's disease by modifying its underlying biology rather than its symptoms, an effort whose overall yield has been low.(2) What distinguishes the gingipain approach is its basis in a specific, detectable pathogen and a plausible causal mechanism, which allows patient selection and target engagement to be measured directly.(15) If a biomarker-selected population can be identified in which gingipain load predicts response, this class of drug could occupy a niche that amyloid-directed therapies have struggled to fill.(45)
Periodontal treatment offers a complementary and widely available intervention. In rats with streptozotocin-induced Alzheimer-like pathology, experimental periodontitis worsened behavior and raised the hippocampal phosphorylated tau/tau ratio, whereas non-surgical periodontal therapy restored behavioral performance to control levels and reduced nuclear factor-kappa B.(39) Clinical guidance now frames periodontal care in people with cognitive impairment as both an oral health and a potential neuroprotective measure, while acknowledging that efficacy on cognition has not been demonstrated in humans.(46,47)
Study | Model or population | Intervention | Main outcome |
|---|---|---|---|
Dominy et al. 2019 | Wild-type mice | Small-molecule gingipain inhibitors | Reduced Pg brain load, amyloid-beta and neuroinflammation |
Detke et al. 2021 | Phase 2/3 GAIN trial, mild to moderate AD | Atuzaginstat (COR388) 40 or 80 mg twice daily | Baseline data; primary endpoints later missed in the overall population |
Detke et al. 2023 | Phase 1 SAD/MAD in healthy volunteers | LHP588, second-generation inhibitor | Safety and tolerability data for a brain-penetrant lysine-gingipain inhibitor |
Yavuz et al. 2025 | Rats with Alzheimer-like pathology | Experimental periodontitis with and without NSPT | NSPT restored behavior and reduced NF-kappa B; periodontitis raised the hippocampal p-tau/tau ratio |
Zhao et al. 2023 | Polymicrobial mouse periodontitis | Nisin (lantibiotic) | Reduced brain pathogen DNA, pro-inflammatory cytokines, amyloid-beta 42 and tau |
Note: AD = Alzheimer's disease; NSPT = non-surgical periodontal therapy; SAD/MAD = single and multiple ascending dose. Source: Elaborated by the authors from the reviewed studies.
DISCUSSION
This review converges on three findings. The epidemiological association between periodontitis, tooth loss and cognitive decline is consistent and dose-responsive, with risk increments of roughly 50% to 65% in pooled analyses, but it carries only low to moderate certainty. The experimental evidence identifies the P. gingivalis gingipains as the molecular component most consistently linked to blood-brain barrier disruption, microglial activation and amyloid and tau pathology. Neuroinflammation is the pathway that unifies these observations, and it is the target through which gingipain inhibitors and periodontal treatment are being tested.
These conclusions agree with several recent syntheses that describe P. gingivalis as a plausible contributor to Alzheimer's disease rather than an incidental finding.(11,48,49) One early synthesis framed the bacterium as a strong risk factor on the basis of its capacity to cleave the amyloid-beta precursor protein and tau in vitro and to reproduce hallmark lesions in animal models, a position the present evidence still supports in broad terms.(50) Systematic reviews that applied explicit eligibility criteria likewise concluded that the bacterium is a risk factor with a reproducible, if heterogeneous, association with Alzheimer's disease.(51-53) The oral-brain axis framework, in which chronic oral dysbiosis sustains systemic inflammation and the circulation of bacterial products, accommodates the human postmortem and animal data assembled here.(54-56)
Other reviewers are more cautious. Jungbauer and colleagues emphasized that a causative relationship remains unproven, because human studies are observational, postmortem detection does not establish direction, and animal models use exposure protocols that exceed natural infection.(11) A narrative review of central and extra-central nervous system infections reached the same general conclusion for microbial hypotheses of neurodegeneration, namely that infection is associated with, but not yet established as a cause of, the disease.(57) The inconclusive findings for periodontitis in some Health 2000 analyses and the null pooled estimate for dementia in one meta-analysis illustrate why the association should not be overstated.(10,17) The GAIN trial result is the most informative negative: a molecule with strong preclinical rationale did not benefit the overall population, which suggests either that gingipains are not a dominant driver in established disease, that the treated population was too advanced, or that the dose and design were inadequate.(45)
A further interpretive question concerns directionality. Poor oral health is both a possible upstream exposure and a downstream consequence of dementia, because declining manual dexterity, dependence for hygiene and reduced dental attendance all worsen periodontal status in people with cognitive impairment.(58) The bidirectional relationship does not invalidate the oral-to-brain hypothesis, but it complicates the interpretation of cross-sectional associations and reinforces the need for longitudinal designs that model reverse causality, as several of the cohorts reviewed here attempted.(21)
The mechanisms assembled here are biologically coherent. Gingipains degrade tight junction proteins, open the blood-brain barrier and enter neurons, where they cleave substrates that aggregate in disease.(12,14) Their activation of microglia through protease-activated receptor 2 provides a receptor-level explanation for the neuroinflammation observed across models.(13) The antimicrobial function of amyloid-beta supplies an evolutionary rationale for why a chronic oral infection might accelerate amyloid deposition.(15,37) Together, these data support a model in which gingipains initiate and perpetuate a neuroinflammatory loop rather than a single-hit causal pathway.
The contribution of this synthesis is to place neuroinflammation, rather than amyloid alone, at the center of the periodontitis-Alzheimer's axis. Earlier reviews emphasized the detection of the bacterium or the epidemiological association; by tracing the gingipain-to-microglia-to-neuron sequence, this review makes explicit the receptor-level and organelle-level steps that remain to be tested in humans.(4,13) That framing also identifies the most informative next experiments: human microglial studies of gingipain exposure, and longitudinal cohorts that measure gingipain biomarkers before the onset of cognitive symptoms.
Prevention also deserves attention, because the axis is potentially actionable long before dementia appears. If the cumulative exposure model is correct, controlling periodontitis in midlife could reduce the burden of neuroinflammation in later decades, and oral hygiene, smoking cessation and regular periodontal maintenance are all established, low-risk measures.(46) The oral microbiome is also modifiable by probiotics and bacteriocins, as the nisin experiments illustrate, although these remain far from clinical application.(43) These considerations support the inclusion of periodontal health in multifactorial dementia prevention programs, without implying that oral care alone can prevent the disease.
The infectious hypothesis of Alzheimer's disease has gained ground as the amyloid cascade has struggled to explain sporadic cases, and the present axis is one of its most concrete instantiations.(37) Unlike more diffuse claims about the microbiome, the gingipain hypothesis names a molecule, a target cell and a therapeutic agent, which makes it falsifiable in a way that broad dysbiosis hypotheses are not.(15) This specificity is an asset for research even if the hypothesis ultimately fails, because negative trials of gingipain inhibition carry more interpretive weight than negative associations alone.(45)
The strengths of this synthesis are its span across human postmortem, epidemiological and experimental evidence, and its restriction to literature published within the review window, which reduces the risk of relying on superseded findings. The argument matrix forced each claim to be matched to supporting and opposing studies, which makes the points of convergence and disagreement explicit.
This review has limitations. The search was not systematic, so relevant studies may have been missed; a preregistered systematic review with formal risk-of-bias assessment would quantify this. Only abstracts in English and Spanish were synthesized in detail, which may bias toward high-income settings; multilingual screening would improve generalizability. The synthesis relies heavily on animal models whose exposure routes differ from natural periodontal disease; standardized models with physiological inocula would strengthen causal claims. Postmortem evidence is correlational, and the epidemiological estimates are vulnerable to residual confounding; triangulation with genetic instruments such as Mendelian randomization is the most direct way to address this. Finally, the clinical data on gingipain inhibition are immature; the LHP588 phase 2 program and trials of periodontal treatment with cognitive endpoints should be tracked.( 45,46)
For periodontal medicine, the immediate implication is conservative: clinicians should treat periodontitis on its own merits and can reasonably describe its treatment as part of brain-health promotion without overstating the evidence.(46) Screening questions about oral health in memory clinics, and about cognitive concerns in dental settings, are inexpensive and may identify patients who warrant coordinated care.(47) None of these measures requires proof of causation, but all of them follow from the strength and coherence of the association documented here.
For clinical practice, the evidence supports treating periodontitis as a modifiable exposure that plausibly influences cognitive trajectories, and as a condition that deserves prompt treatment in older adults regardless of its cerebral effects. These actions are consistent with the direction of the current evidence and do not depend on resolving the question of causality. Dental professionals are well placed to intervene early, because periodontitis is detectable and treatable years before cognitive symptoms appear, and because the same patients who develop Alzheimer's disease are precisely those who accumulate periodontal damage with age.(46,47) For research, the priorities are biomarkers that measure gingipain load in accessible fluids, trials enriched for participants with detectable oral P. gingivalis, and periodontal interventions with prespecified cognitive outcomes.
CONCLUSIONS
Epidemiological studies, including meta-analyses and prospective cohorts, consistently associate periodontitis and tooth loss with cognitive decline and dementia, although the certainty of the evidence is low to moderate and residual confounding cannot be excluded. P. gingivalis reaches the central nervous system through bacteremia, the trigeminal nerve and outer membrane vesicles, and its gingipains are detected in postmortem brains of people with Alzheimer's disease, where they localize to neurons and to tau pathology. Neuroinflammation, driven by microglial activation through protease-activated receptor 2 together with oxidative and mitochondrial injury, is the pathway that best links gingipain activity to neurodegeneration in experimental models. Gingipain inhibition reduces pathology in animal models, but the phase 2/3 trial of atuzaginstat did not meet its primary endpoint, and periodontal treatment, although biologically plausible, has not yet been shown to protect cognition in humans. The periodontitis-Alzheimer's disease axis is therefore best regarded as a plausible and therapeutically relevant pathway whose causal status in humans remains to be established.
References
- 1 Winston Wong P. Economic burden of Alzheimer disease and managed care considerations. Am J Manag Care. 2020;26(Suppl 8):S177-S183. doi: 10.37765/ajmc.2020.88482
- 2 Long JM, Holtzman DM. Alzheimer Disease: An Update on Pathobiology and Treatment Strategies. Cell. 2019;179(2):312-339. doi: 10.1016/j.cell.2019.09.001
- 3 Butler CA, Ciccotosto GD, Rygh N, Bijlsma E, Dashper SG, Brown AC. Bacterial Membrane Vesicles: The Missing Link Between Bacterial Infection and Alzheimer Disease. The Journal of Infectious Diseases. 2024;230(Supplement_2):S87-S94. doi: 10.1093/infdis/jiae228
- 4 Verma A, Azhar G, Zhang X, Patyal P, Kc G, Sharma S, et al. P. gingivalis-LPS Induces Mitochondrial Dysfunction Mediated by Neuroinflammation through Oxidative Stress. IJMS. 2023;24(2):950. doi: 10.3390/ijms24020950
- 5 Bulgart HR, Neczypor EW, Wold LE, Mackos AR. Microbial involvement in Alzheimer disease development and progression. Mol Neurodegeneration. 2020;15(1):42. doi: 10.1186/s13024-020-00378-4
- 6 Dominy SS, Lynch C, Ermini F, Benedyk M, Marczyk A, Konradi A, et al. Porphyromonas gingivalis in Alzheimer’s disease brains: Evidence for disease causation and treatment with small-molecule inhibitors. Sci Adv. 2019;5(1):eaau3333. doi: 10.1126/sciadv.aau3333
- 7 Ilievski V, Zuchowska PK, Green SJ, Toth PT, Ragozzino ME, Le K, et al. Chronic oral application of a periodontal pathogen results in brain inflammation, neurodegeneration and amyloid beta production in wild type mice. PLoS ONE. 2018;13(10):e0204941. doi: 10.1371/journal.pone.0204941
- 8 Qadir BH, Mahmood MK, Amin YMM, Kurda HA, Rasheed TA, Noori AH, et al. Periodontitis and Tooth Loss Are Associated With Higher Risks of Cognitive Disorders: A Systematic Umbrella Meta‐Analysis. Clinical & Exp Dental Res. 2025;11(6):e70240. doi: 10.1002/cre2.70240
- 9 Singhrao SK, Olsen I. Are Porphyromonas gingivalis Outer Membrane Vesicles Microbullets for Sporadic Alzheimer’s Disease Manifestation?. Journal of Alzheimer's Disease Reports. 2018;2(1):219-228. doi: 10.3233/adr-180080
- 10 Asher S, Suominen AL, Stephen R, Ngandu T, Koskinen S, Solomon A. Clinical and Radiological Markers of Periodontal Status and Risk of Cognitive Decline and Incident Dementia. J Clinic Periodontology. 2025;52(8):1082-1098. doi: 10.1111/jcpe.14173
- 11 Jungbauer G, Stähli A, Zhu X, Auber Alberi L, Sculean A, Eick S. Periodontal microorganisms and Alzheimer disease – A causative relationship?. Periodontology 2000. 2022;89(1):59-82. doi: 10.1111/prd.12429
- 12 Nonaka S, Kadowaki T, Nakanishi H. Secreted gingipains from Porphyromonas gingivalis increase permeability in human cerebral microvascular endothelial cells through intracellular degradation of tight junction proteins. Neurochemistry International. 2022;154:105282. doi: 10.1016/j.neuint.2022.105282
- 13 Nonaka S, Nakanishi H. Secreted gingipains from Porphyromonas gingivalis induce microglia migration through endosomal signaling by protease-activated receptor 2. Neurochemistry International. 2020;140:104840. doi: 10.1016/j.neuint.2020.104840
- 14 Haditsch U, Roth T, Rodriguez L, Hancock S, Cecere T, Nguyen M, et al. Alzheimer’s Disease-Like Neurodegeneration in Porphyromonas gingivalis Infected Neurons with Persistent Expression of Active Gingipains. Journal of Alzheimer’s Disease. 2020;75(4):1361-1376. doi: 10.3233/jad-200393
- 15 Sabbagh MN, Decourt B. COR388 (atuzaginstat): an investigational gingipain inhibitor for the treatment of Alzheimer disease. Expert Opinion on Investigational Drugs. 2022;31(10):987-993. doi: 10.1080/13543784.2022.2117605
- 16 Detke M. An update and baseline data from the phase 2/3 GAIN trial of COR388 (atuzaginstat), a novel bacterial virulence factor inhibitor for the treatment of Alzheimer’s disease. Alzheimer's & Dementia. 2021;17(S9):e050624. doi: 10.1002/alz.050624
- 17 Guo H, Chang S, Pi X, Hua F, Jiang H, Liu C, et al. The Effect of Periodontitis on Dementia and Cognitive Impairment: A Meta-Analysis. IJERPH. 2021;18(13):6823. doi: 10.3390/ijerph18136823
- 18 Li L, Zhang Q, Yang D, Yang S, Zhao Y, Jiang M, et al. Tooth loss and the risk of cognitive decline and dementia: A meta-analysis of cohort studies. Front Neurol. 2023;14:1103052. doi: 10.3389/fneur.2023.1103052
- 19 Nilsson H, Sanmartin Berglund J, Renvert S. Longitudinal evaluation of periodontitis and development of cognitive decline among older adults. J Clinic Periodontology. 2018;45(10):1142-1149. doi: 10.1111/jcpe.12992
- 20 Arévalo-Caro C, López D, Sánchez Milán JA, Lorca C, Mulet M, Arboleda H, et al. Periodontal Indices as Predictors of Cognitive Decline: Insights from the PerioMind Colombia Cohort. Biomedicines. 2025;13(1):205. doi: 10.3390/biomedicines13010205
- 21 Asher S, Suominen AL, Stephen R, Ngandu T, Koskinen S, Solomon A. Association of tooth location, occlusal support and chewing ability with cognitive decline and incident dementia. J Clinic Periodontology. 2025;52(1):24-39. doi: 10.1111/jcpe.13970
- 22 Rubinstein T, Brickman AM, Cheng B, Burkett S, Park H, Annavajhala MK, et al. Periodontitis and brain magnetic resonance imaging markers of Alzheimer's disease and cognitive aging. Alzheimer's & Dementia. 2024;20(3):2191-2208. doi: 10.1002/alz.13683
- 23 Botelho J, Leira Y, Viana J, Machado V, Lyra P, Aldrey JM, et al. The Role of Inflammatory Diet and Vitamin D on the Link between Periodontitis and Cognitive Function: A Mediation Analysis in Older Adults. Nutrients. 2021;13(3):924. doi: 10.3390/nu13030924
- 24 Dziedzic A. Is Periodontitis Associated with Age-Related Cognitive Impairment? The Systematic Review, Confounders Assessment and Meta-Analysis of Clinical Studies. IJMS. 2022;23(23):15320. doi: 10.3390/ijms232315320
- 25 Nascimento PC, Castro MML, Magno MB, Almeida APCPSC, Fagundes NCF, Maia LC, et al. Association Between Periodontitis and Cognitive Impairment in Adults: A Systematic Review. Front Neurol. 2019;10:323. doi: 10.3389/fneur.2019.00323
- 26 Ermini F, Low VF, Song JJ, Tan AYS, Faull RLM, Dragunow M, et al. Ultrastructural localization of Porphyromonas gingivalis gingipains in the substantia nigra of Parkinson’s disease brains. npj Parkinsons Dis. 2024;10(1):90. doi: 10.1038/s41531-024-00705-2
- 27 Lei S, Li J, Yu J, Li F, Pan Y, Chen X, et al. Porphyromonas gingivalis bacteremia increases the permeability of the blood-brain barrier via the Mfsd2a/Caveolin-1 mediated transcytosis pathway. Int J Oral Sci. 2023;15(1):3. doi: 10.1038/s41368-022-00215-y
- 28 Zhang Z, Liu D, Liu S, Zhang S, Pan Y. The Role of Porphyromonas gingivalis Outer Membrane Vesicles in Periodontal Disease and Related Systemic Diseases. Front Cell Infect Microbiol. 2021;10:585917. doi: 10.3389/fcimb.2020.585917
- 29 Ma X, Shin YJ, Yoo JW, Park HS, Kim DH. Extracellular vesicles derived from Porphyromonas gingivalis induce trigeminal nerve-mediated cognitive impairment. Journal of Advanced Research. 2023;54:293-303. doi: 10.1016/j.jare.2023.02.006
- 30 Mieszkowska A, Marcinkowska M, Widziolek M, Potempa J, Chadzinska M. Porphromonas gingivalis infection induces gingipain-dependent changes in the brain vasculature of zebrafish larvae. Cell Commun Signal. 2025;23(1):552. doi: 10.1186/s12964-025-02557-6
- 31 Díaz-Zúñiga J, More J, Melgar-Rodríguez S, Jiménez-Unión M, Villalobos-Orchard F, Muñoz-Manríquez C, et al. Alzheimer’s Disease-Like Pathology Triggered by Porphyromonas gingivalis in Wild Type Rats Is Serotype Dependent. Front Immunol. 2020;11:588036. doi: 10.3389/fimmu.2020.588036
- 32 Ciccotosto GD, Mohammed AI, Paolini R, Bijlsma E, Toulson S, Holden J, et al. Chronic Oral Inoculation of Porphyromonas gingivalis and Treponema denticola Induce Different Brain Pathologies in a Mouse Model of Alzheimer Disease. The Journal of Infectious Diseases. 2024;230(Supplement_2):S109-S116. doi: 10.1093/infdis/jiae286
- 33 Bahar B, Kanagasingam S, Tambuwala MM, Aljabali AAA, Dillon SA, Doaei S, et al. Porphyromonas gingivalis (W83) Infection Induces Alzheimer’s Disease-Like Pathophysiology in Obese and Diabetic Mice. JAD. 2021;82(3):1259-1275. doi: 10.3233/jad-210465
- 34 Visentin D, Gobin I, Maglica Ž. Periodontal Pathogens and Their Links to Neuroinflammation and Neurodegeneration. Microorganisms. 2023;11(7):1832. doi: 10.3390/microorganisms11071832
- 35 Jia L, Han N, Du J, Guo L, Luo Z, Liu Y. Pathogenesis of Important Virulence Factors of Porphyromonas gingivalis via Toll-Like Receptors. Front Cell Infect Microbiol. 2019;9:262. doi: 10.3389/fcimb.2019.00262
- 36 Chow YC, Yam HC, Gunasekaran B, Lai WY, Wo WY, Agarwal T, et al. Implications of Porphyromonas gingivalis peptidyl arginine deiminase and gingipain R in human health and diseases. Front Cell Infect Microbiol. 2022;12:987683. doi: 10.3389/fcimb.2022.987683
- 37 Vojtechova I, Machacek T, Kristofikova Z, Stuchlik A, Petrasek T. Infectious origin of Alzheimer’s disease: Amyloid beta as a component of brain antimicrobial immunity. PLoS Pathog. 2022;18(11):e1010929. doi: 10.1371/journal.ppat.1010929
- 38 Pedrosa ME, Martin V, Fernandes MH, Gomes PS. Gingipain inhibitors as an innovative therapy for periodontal and associated-systemic diseases: a systematic review. Clin Oral Invest. 2025;29(9):418. doi: 10.1007/s00784-025-06472-5
- 39 Yavuz S, Elibol B, Demir E, Kinsiz B, Toluk O, Gunpinar S. Effects of Experimental Periodontitis and Periodontal Treatment on Alzheimer‐Like Pathology in Rats. Oral Diseases. 2025;31(12):3461-3473. doi: 10.1111/odi.70001
- 40 Zhang W, Xiao D, Mao Q, Xia H. Role of neuroinflammation in neurodegeneration development. Sig Transduct Target Ther. 2023;8(1):267. doi: 10.1038/s41392-023-01486-5
- 41 Ding Y, Ren J, Yu H, Yu W, Zhou Y. Porphyromonas gingivalis, a periodontitis causing bacterium, induces memory impairment and age-dependent neuroinflammation in mice. Immun Ageing. 2018;15(1):6. doi: 10.1186/s12979-017-0110-7
- 42 Chi L, Cheng X, Lin L, Yang T, Sun J, Feng Y, et al. Porphyromonas gingivalis-Induced Cognitive Impairment Is Associated With Gut Dysbiosis, Neuroinflammation, and Glymphatic Dysfunction. Front Cell Infect Microbiol. 2021;11:755925. doi: 10.3389/fcimb.2021.755925
- 43 Zhao C, Kuraji R, Ye C, Gao L, Radaic A, Kamarajan P, et al. Nisin a probiotic bacteriocin mitigates brain microbiome dysbiosis and Alzheimer’s disease-like neuroinflammation triggered by periodontal disease. J Neuroinflammation. 2023;20(1):228. doi: 10.1186/s12974-023-02915-6
- 44 Tran VTA, Lee LP, Cho H. Neuroinflammation in neurodegeneration via microbial infections. Front Immunol. 2022;13:907804. doi: 10.3389/fimmu.2022.907804
- 45 Detke M, Sabbagh M, Holsinger LJ, Bolger J, Wang J, Ryder M, et al. Phase 2 Study Design and New Data from the Phase 1 SAD/MAD Trial of LHP588, A Second‐Generation Gingipain Inhibitor for the Treatment of P. Gingivalis ‐ Positive Alzheimer Dementia. Alzheimer's & Dementia. 2023;19(S24):e082502. doi: 10.1002/alz.082502
- 46 Chalmers JC, Hernandez‐Kapila YL. The role of the oral microbiome, host response, and periodontal disease treatment in Alzheimer's disease: A primer. Periodontology 2000. 2025;98(1):220-227. doi: 10.1111/prd.12631
- 47 Ryder MI. Porphyromonas gingivalis and Alzheimer disease: Recent findings and potential therapies. Journal of Periodontology. 2020;91(S1):S45-S49. doi: 10.1002/jper.20-0104
- 48 Huang Z, Hao M, Shi N, Wang X, Yuan L, Yuan H, et al. Porphyromonas gingivalis: a potential trigger of neurodegenerative disease. Front Immunol. 2025;16:1482033. doi: 10.3389/fimmu.2025.1482033
- 49 Shawkatova I, Durmanova V, Javor J. Alzheimer’s Disease and Porphyromonas gingivalis: Exploring the Links. Life. 2025;15(1):96. doi: 10.3390/life15010096
- 50 Kanagasingam S, Chukkapalli SS, Welbury R, Singhrao SK. Porphyromonas gingivalis is a Strong Risk Factor for Alzheimer’s Disease. Journal of Alzheimer's Disease Reports. 2020;4(1):501-511. doi: 10.3233/adr-200250
- 51 Elwishahy A, Antia K, Bhusari S, Ilechukwu NC, Horstick O, Winkler V. Porphyromonas Gingivalis as a Risk Factor to Alzheimer’s Disease: A Systematic Review. Journal of Alzheimer's Disease Reports. 2021;5(1):721-732. doi: 10.3233/adr-200237
- 52 Sarmiento-Ordóñez JM, Brito-Samaniego D, Vásquez-Palacios AC, Pacheco-Quito EM. Association Between Porphyromonas gingivalis and Alzheimer’s Disease: A Comprehensive Review. IDR. 2025;Volume 18:2119-2136. doi: 10.2147/idr.s491628
- 53 Inchingolo AM, Inchingolo AD, Piras F, Avantario P, Ferrante L, Paduanelli G, et al. Oral Health and Cognitive Decline: A Systematic Review of the Periodontitis–Alzheimer’s Connection. Applied Sciences. 2025;15(12):6728. doi: 10.3390/app15126728
- 54 Felicetti A, Azzolino D, Piro PP, Lopes GCD, Rezaeinezhad N, Lovero R, et al. The Oral–Brain Axis in Alzheimer’s Disease: From Microbial Dysbiosis to Neurodegeneration. Microorganisms. 2025;13(12):2741. doi: 10.3390/microorganisms13122741
- 55 Rozenblum G, Ait‐Aissa K, Zahran G, Alipour M, Sahyoun AM, Munkhsaikhan U, et al. Unraveling the oral microbiome's role in Alzheimer's disease: From pathophysiology to therapeutic potential. Alzheimer's & Dementia. 2025;21(12):e71011. doi: 10.1002/alz.71011
- 56 Adil NA, Omo-Erigbe C, Yadav H, Jain S. The Oral–Gut Microbiome–Brain Axis in Cognition. Microorganisms. 2025;13(4):814. doi: 10.3390/microorganisms13040814
- 57 Kettunen P, Koistinaho J, Rolova T. Contribution of CNS and extra-CNS infections to neurodegeneration: a narrative review. J Neuroinflammation. 2024;21(1):152. doi: 10.1186/s12974-024-03139-y
- 58 Liccardo D, Marzano F, Carraturo F, Guida M, Femminella GD, Bencivenga L, et al. Potential Bidirectional Relationship Between Periodontitis and Alzheimer’s Disease. Front Physiol. 2020;11:683. doi: 10.3389/fphys.2020.00683
Declarations
Funding
No financing
Conflict of interest
None
Authorship contributions
Drafting – original draft: Ana Rodríguez Yanes.
Writing–review and editing: Ana Rodríguez Yanes.